
ESOGASTRIC SURGERY
Hiatal Hernia
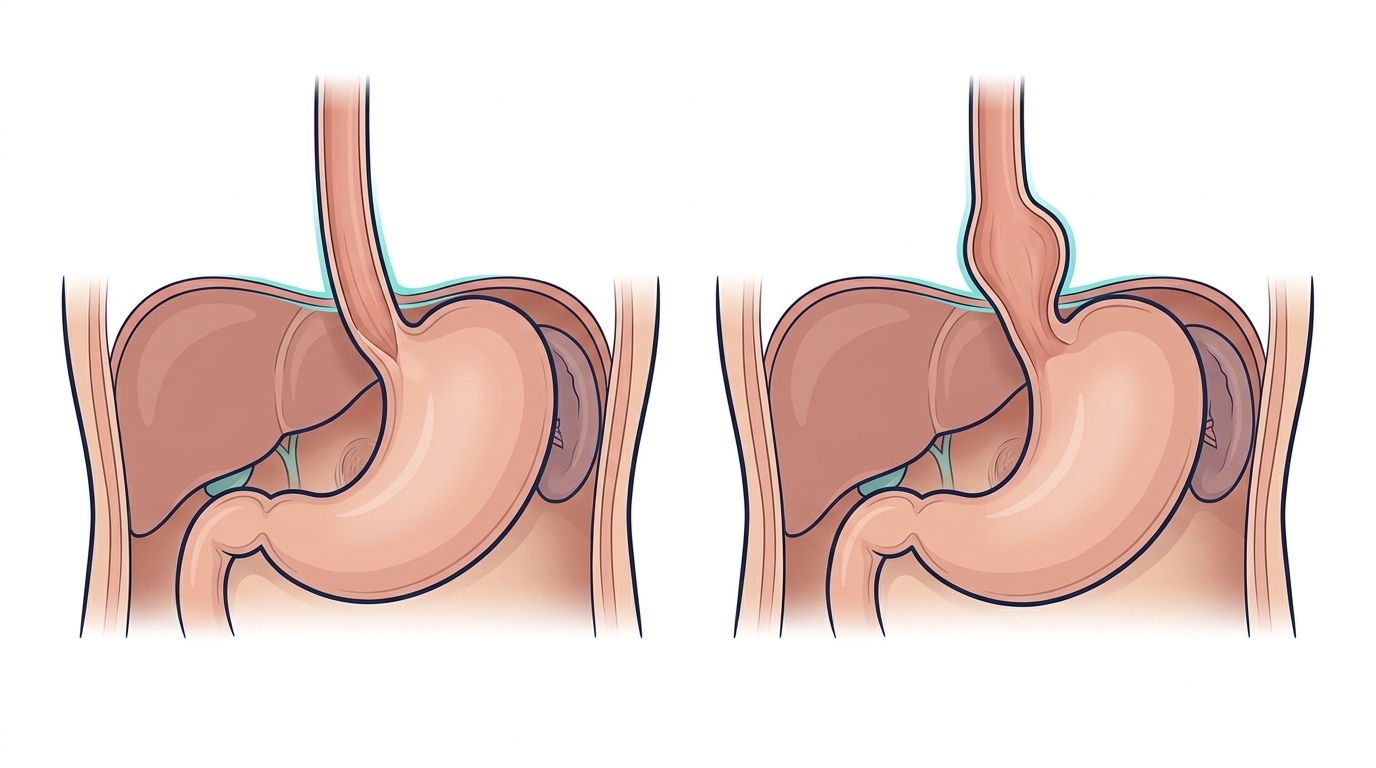
When the upper part of the stomach moves up through the diaphragm.
Une hernie hiatale apparaît lorsqu’une partie de l’estomac remonte à travers l’orifice du diaphragme normalement traversé par l’œsophage.
Très fréquente, elle peut être découverte fortuitement ou être associée à différents symptômes, notamment un reflux gastro-œsophagien, des régurgitations, une gêne après les repas ou, dans certaines formes plus importantes, des symptômes thoraciques ou digestifs.
Toutes les hernies hiatales ne nécessitent pas une intervention. Leur prise en charge dépend notamment du type de hernie, de sa taille, des symptômes et des résultats du bilan.
What Is a Hiatal Hernia?
Part of the Stomach Moves Up Through the Diaphragm
The chest and abdomen are separated by a muscle called the diaphragm.
The esophagus naturally passes through this muscle via a small opening called the esophageal hiatus, before joining the stomach in the abdomen.
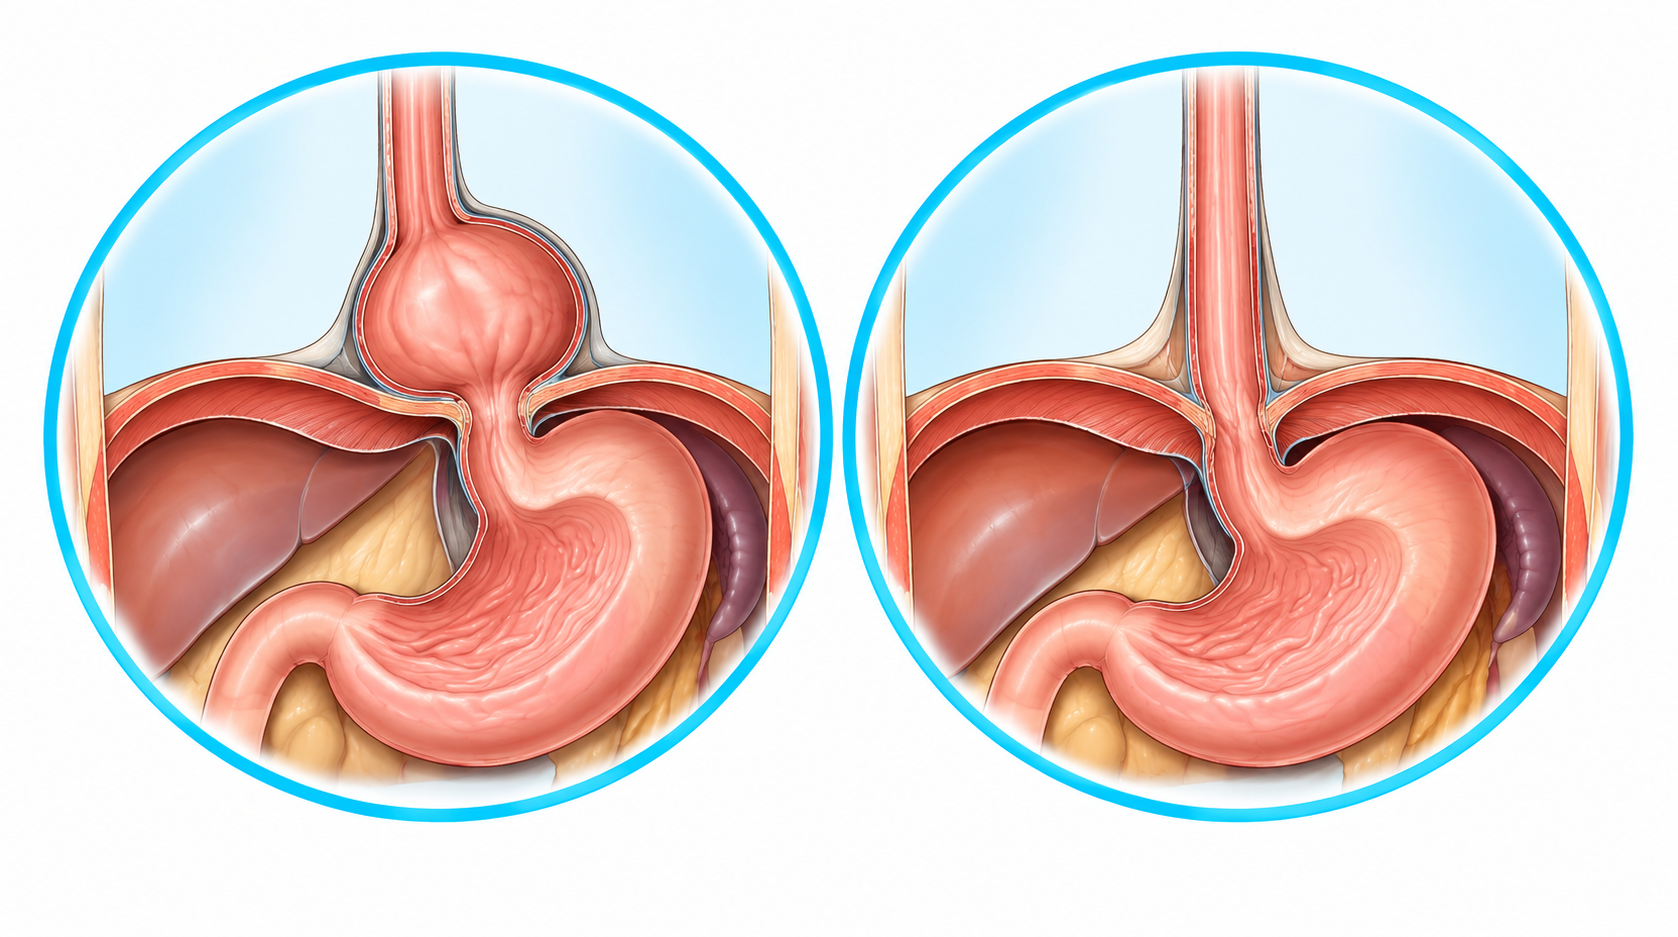
When part of the stomach moves up through this opening into the chest, this is called a hiatal hernia.
The most common form is the sliding hiatal hernia, in which the junction between the esophagus and the stomach moves up above the diaphragm.
A hiatal hernia and gastroesophageal reflux are two different conditions, even though they are frequently associated.
Understand gastroesophageal reflux disease →
Are There Different Types of Hiatal Hernia?
Not All Hiatal Hernias Are the Same
Four types of hiatal hernia are classically distinguished.
Type I
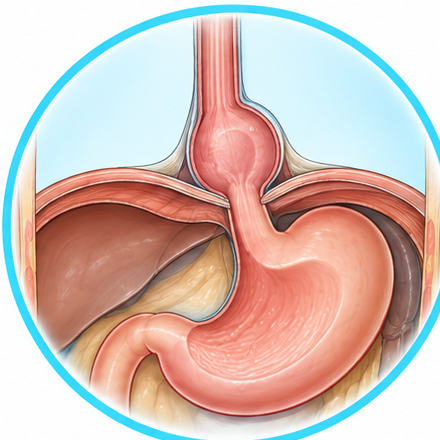
Sliding Hernia
The junction between the esophagus and the stomach moves up above the diaphragm. This is the most common form and the one most frequently associated with gastroesophageal reflux.
Type II
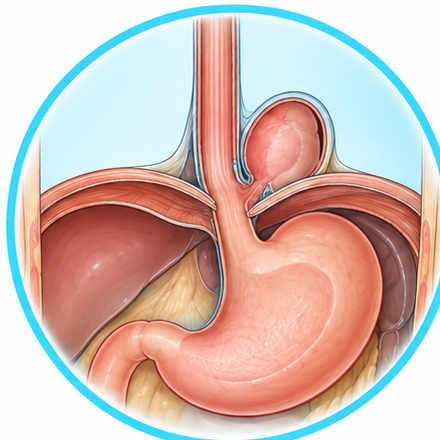
Paraesophageal Hernia
The esophagogastric junction remains in place, but part of the stomach moves up alongside the esophagus.
Type III
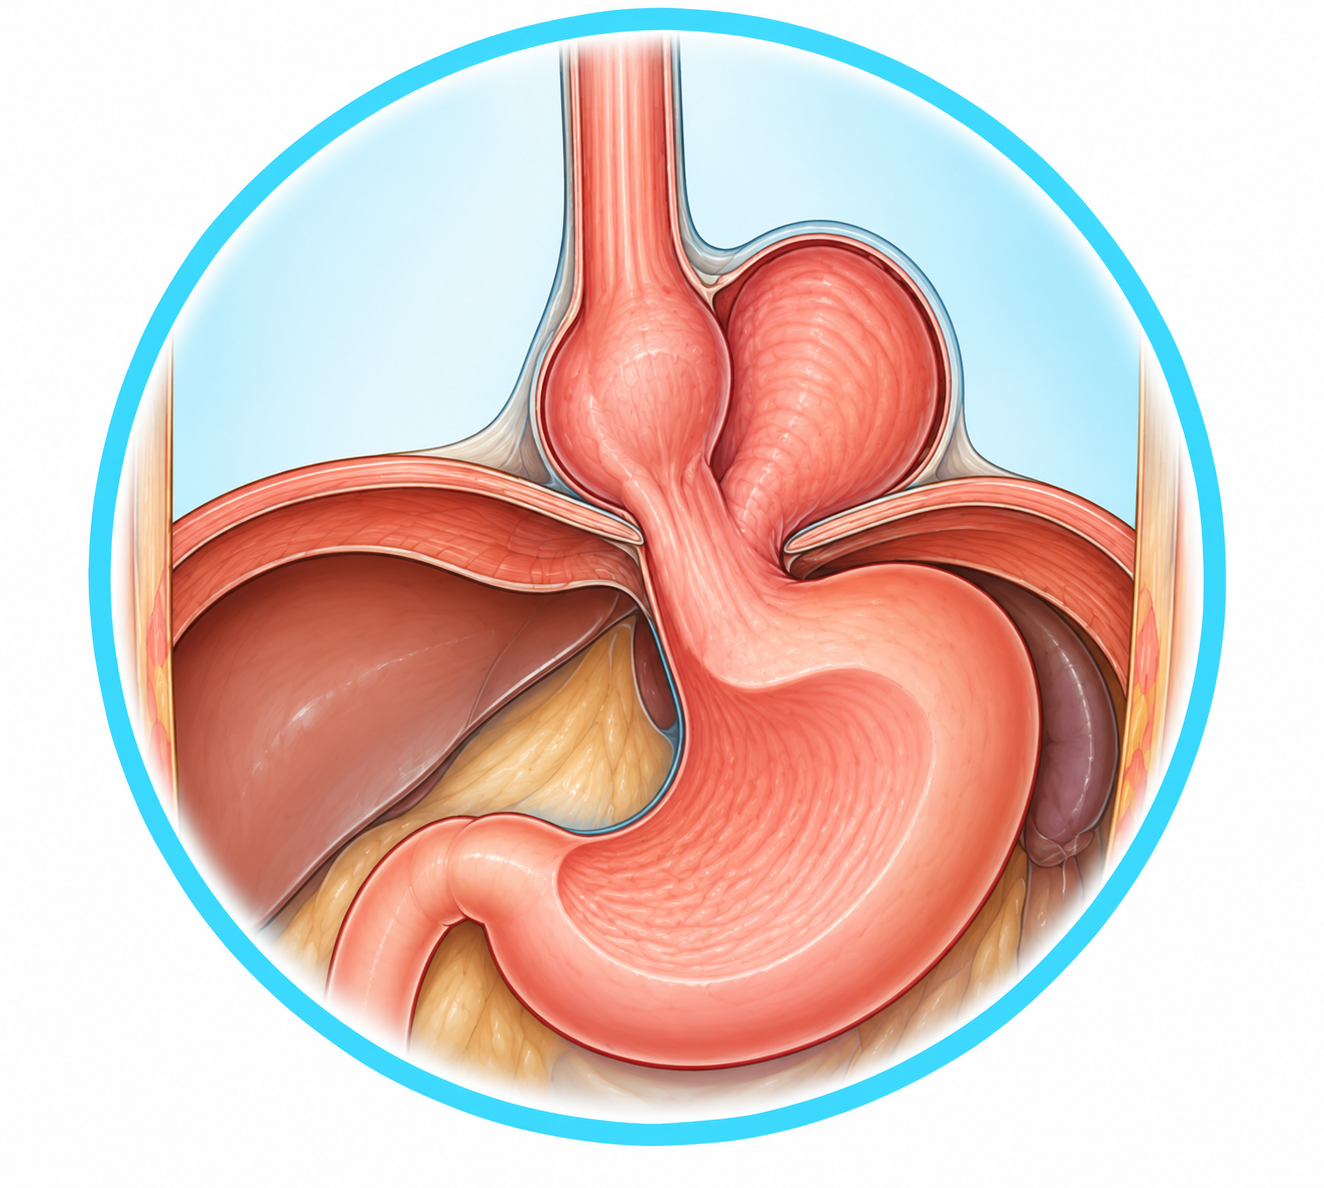
Mixed Hernia
It combines the characteristics of types I and II: the esophagogastric junction and a larger part of the stomach move up above the diaphragm.
Type IV
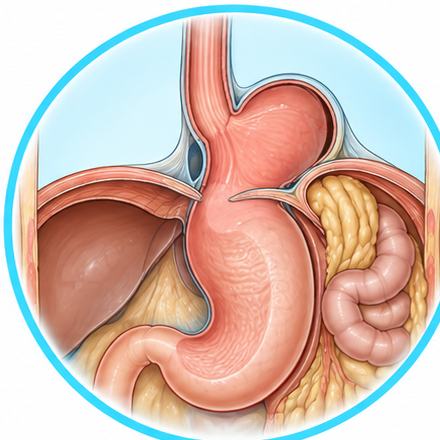
Complex Hernia
In the most severe forms, other abdominal structures may also move up through the hiatus.
What Symptoms Can a Hiatal Hernia Cause?
The Manifestations Can Be Very Different
A small hiatal hernia may cause no symptoms and be discovered during an examination performed for another reason.
When it becomes symptomatic, the manifestations depend in particular on its type, its size, and the possible presence of associated reflux. Larger hernias may also be associated with symptoms such as dysphagia, chest discomfort, dyspnea, or anemia.
Reflux and Regurgitation
Acid or food regurgitation may be associated with certain hiatal hernias.
Discomfort After Meals
A sensation of heaviness, pressure, or discomfort may appear after eating.
Difficulty Swallowing
Difficulty with food passage may be present in certain situations.
Chest or Respiratory Symptoms
Larger hernias may sometimes be associated with chest discomfort, shortness of breath, or other less typical manifestations.
Hiatal Hernia and Reflux: What Is the Difference?
Two Different, Often Associated Conditions
A hiatal hernia is an anatomical abnormality: part of the stomach moves up through the diaphragm.
Gastroesophageal reflux is a functional phenomenon: the contents of the stomach move up into the esophagus.
A hiatal hernia can impair the mechanisms involved in the anti-reflux barrier and thereby promote reflux, but:
one can have a hiatal hernia without significant reflux; and one can have reflux without a hiatal hernia.
The presence of a hiatal hernia is therefore not enough, on its own, to explain all digestive symptoms.
How Is a Hiatal Hernia Diagnosed?
A Work-Up Tailored to the Symptoms and Situation
Depending on the context, several examinations may help characterize the hernia and look for any associated reflux.
Gastroscopy
It allows examination of the esophagus and stomach and helps look for certain associated consequences.
Imaging
An upper gastrointestinal series or other imaging can help clarify the anatomy and extent of certain hernias.

pH Monitoring / Impedance Monitoring
When the question of reflux is significant, these tests can help detect and objectively measure its presence.
Esophageal Manometry
It studies esophageal motility and can be useful, particularly in the work-up preceding certain anti-reflux procedures.
Not all of these tests are necessary for every patient. The work-up is chosen based on symptoms and the strategy being considered.
Does a Hiatal Hernia Always Need to Be Treated?
The Presence of a Hernia Does Not Automatically Mean Surgery Is Needed
No.
A hiatal hernia discovered incidentally and causing no symptoms does not automatically lead to surgery.
The decision depends in particular on the type of hernia, its size, symptoms, associated reflux, and the patient’s overall situation.
For asymptomatic paraesophageal hernias of types II to IV, the available data do not support systematically recommending surgery over surveillance; recent guidelines therefore emphasize an individualized, shared decision.
One does not treat an image: one treats a clinical situation.
When Can Surgery Be Considered?
A Decision Based on Symptoms, Anatomy, and the Work-Up
Surgical repair may be discussed in particular when the hernia is responsible for significant symptoms, when it is associated with objectively confirmed reflux requiring a surgical strategy, or when certain anatomical characteristics justify specific management.
In larger hernias, other manifestations may factor into the decision, including certain eating difficulties, chest discomfort or breathlessness, or, depending on the situation, anemia.
The decision is therefore individualized after analysis of the work-up.
How Is the Surgery Performed?
Repositioning the Stomach and Restoring the Anatomy of the Hiatus
The surgery generally aims to:
- reposition into the abdomen the structures that have moved up into the chest;
- free and correctly reposition the junction between the esophagus and the stomach;
- bring the diaphragmatic crura together to restore an appropriate hiatus around the esophagus;
- depending on the situation, add a procedure aimed at controlling reflux, particularly a fundoplication.
The 2024 SAGES guidelines suggest that fundoplication may be beneficial when repairing type II–IV hiatal hernias, but this recommendation is conditional and based on low-certainty evidence. They do not, however, support systematically recommending for or against the use of mesh at the level of the hiatus.
What About Fundoplication?
An Anti-reflux Procedure That May Be Combined With the Repair
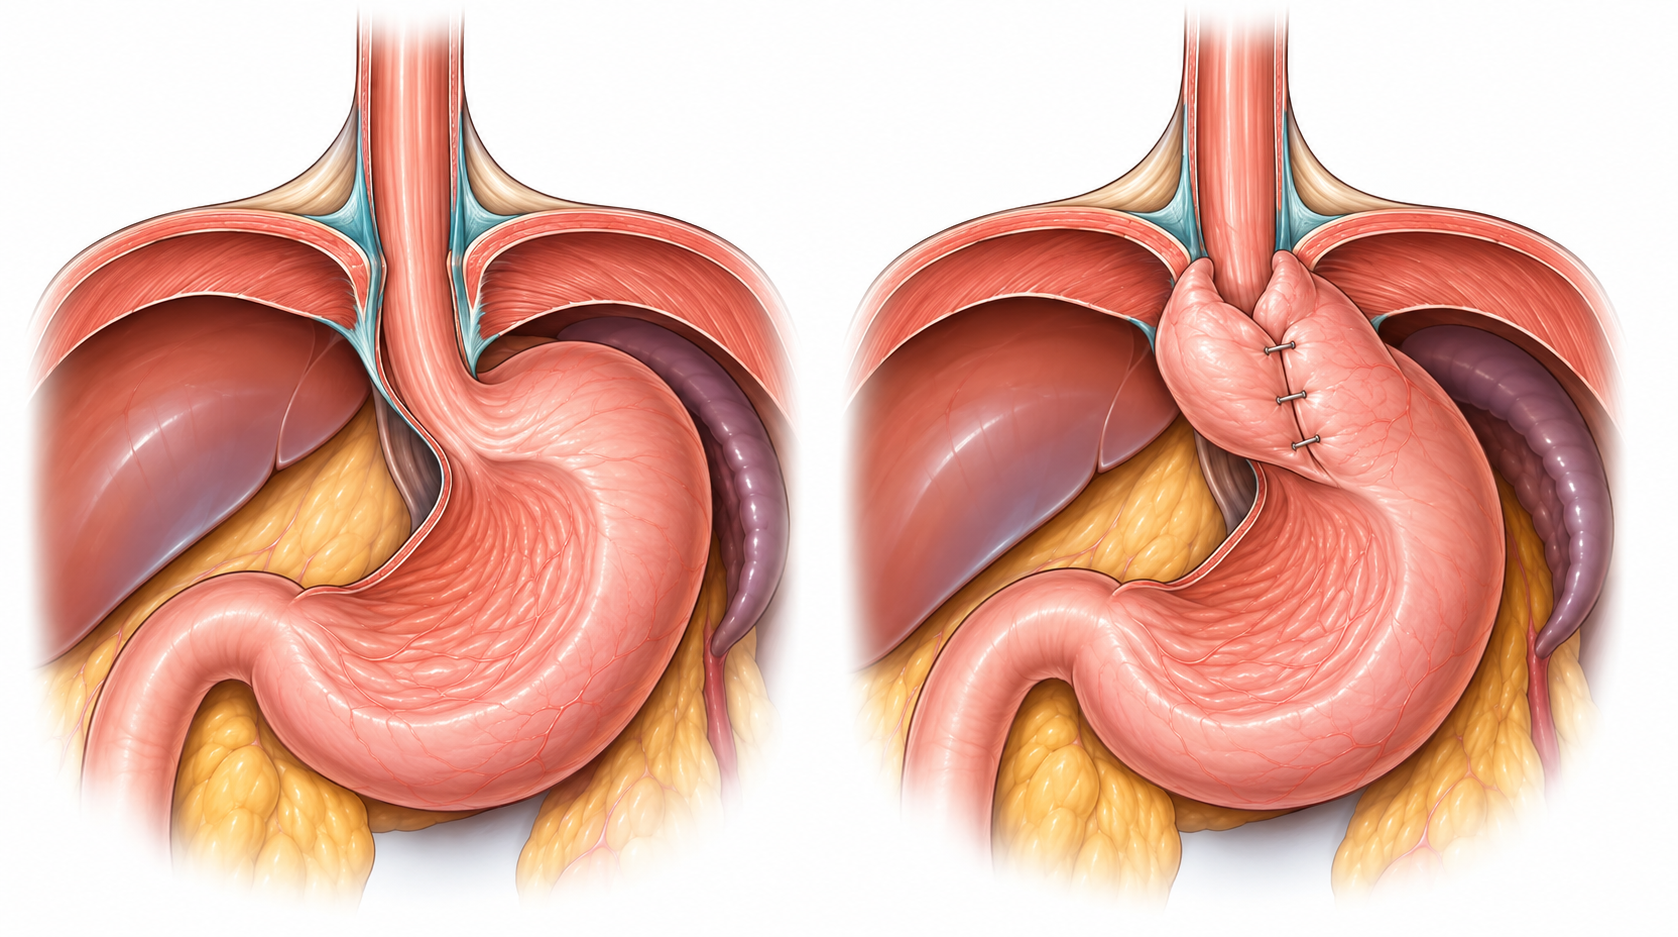
During certain hiatal hernia repairs, a fundoplication may be performed.
It involves using the upper part of the stomach to create a mechanism designed to reinforce the anti-reflux barrier around the lower part of the esophagus.
There are different fundoplication techniques, including complete and partial. The choice depends on the anatomical situation, symptoms, and the results of the functional work-up.
Fundoplication can reduce postoperative reflux, but it is also associated with an increased risk of early dysphagia in the available studies; these factors are therefore part of the individualized discussion.
Minimally Invasive and Robot-Assisted Surgery
Different Technical Approaches May Be Used
Hiatal hernia repair is generally performed using a minimally invasive approach when suited to the situation.
Laparoscopy
Laparoscopy allows the surgeon to operate through several small incisions using a camera and dedicated instruments.
Robot-Assisted Surgery
A robot-assisted approach may also be used in certain situations. It offers the surgeon three-dimensional vision and articulated instruments, while remaining entirely controlled by the surgeon.
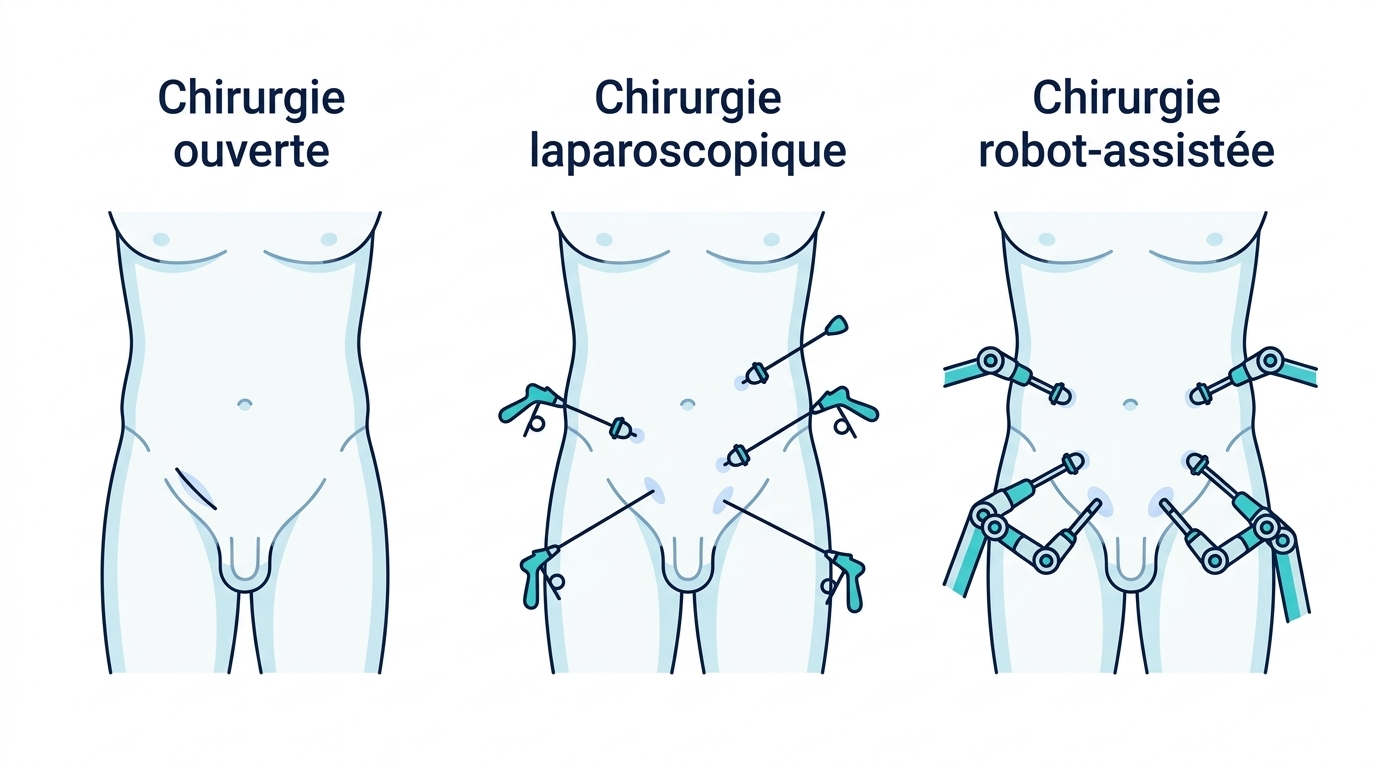
Robotics is a technical means of performing the procedure: it does not, on its own, change the surgical indication.
Both approaches aim to achieve the same surgical goal using small incisions.
What Are the Risks?
Surgery That Requires Personalized Information
As with any surgery, hiatal hernia repair carries risks.
As with any surgical procedure, bleeding or infection can occur.
Dysphagia can occur after surgery and is often transient, but may sometimes require further evaluation.
These can be observed in particular after certain anti-reflux procedures.
Rare but possible during any surgery in this anatomical region.
A hiatal hernia can recur after repair. Available data also show that optimal prevention of recurrence remains an area where certain strategies, particularly the systematic use of mesh, remain debated.
The expected benefits and specific risks are discussed before any surgical decision.
After Surgery
Gradual Resumption of Eating and Activity
After hiatal hernia repair, mobilization is generally encouraged early.
Eating is resumed gradually according to the postoperative protocol and the type of surgery performed.
During the initial healing phase, it may be necessary to temporarily adapt food texture and eating habits.
The resumption of daily activities, work, and sport is then gradual and adapted to recovery.

Personalized Care
Understanding the Hernia Before Deciding on Treatment
The consultation allows for determining the type of hiatal hernia, assessing its extent, and understanding whether the symptoms presented are truly related to it.
When necessary, the work-up is supplemented by examinations to assess the anatomy, the esophagus, and the possible presence of reflux.
Surgery is only proposed when its indication is appropriate to the individual situation.
Dr Pierre Fournier
General and Visceral Surgery
[Actual photo of Dr Fournier — to be added once available]
Frequently Asked Questions:
It corresponds to an anatomical change and generally does not “go away” in the strict sense. Its extent and symptoms can, however, vary.
No. A hiatal hernia and reflux are frequently associated but are not synonymous.
Yes.
No. The decision depends on the type of hernia, symptoms, the work-up, and the individual situation. For certain asymptomatic hernias, current data do not support recommending systematic surgery.
In a sliding hernia, the esophagogastric junction moves up above the diaphragm. In a type II paraesophageal hernia, this junction remains in place while part of the stomach moves up alongside the esophagus.
The work-up depends on the situation and may include a gastroscopy and additional anatomical or functional examinations.
No. The strategy depends on the type of hernia, associated reflux, and the work-up. For operated type II–IV hernias, SAGES guidelines suggest that fundoplication may be beneficial, but with a limited level of evidence.
A robot-assisted approach may be used in certain situations. The robot remains entirely controlled by the surgeon.
Yes. A hiatal hernia, particularly a small one, may cause no symptoms and be discovered incidentally during an examination performed for another reason.
No. Available guidelines do not support systematically recommending for or against the use of mesh at the level of the hiatus; the decision is individualized.
Do You Have a Hiatal Hernia?
Discovering a hiatal hernia does not automatically mean that surgery is necessary.